FeNO stands for Fractional exhaled Nitric Oxide. It’s a simple breath test that measures the level of nitric oxide gas in a patient’s exhaled breath — a marker directly linked to eosinophilic airway inflammation, the type most commonly associated with allergic asthma.
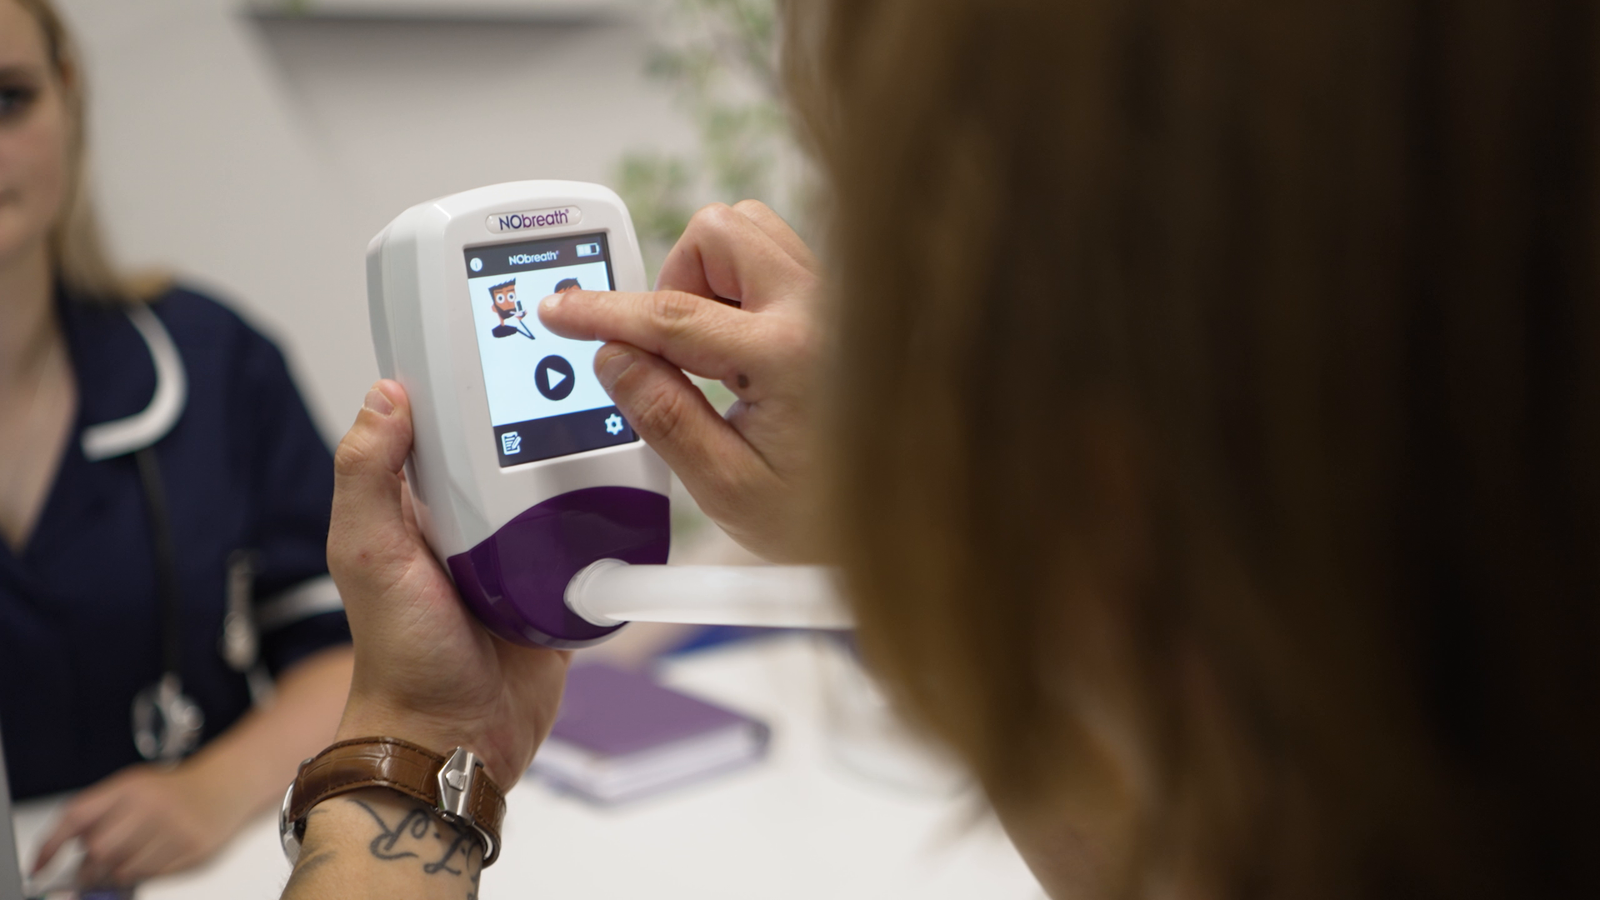
When a patient breathes out steadily into the NObreath monitor’s single-use mouthpiece, the device analyzes the sample and displays a result in parts per billion (ppb) within seconds. Higher FeNO levels generally indicate greater airway inflammation, while lower levels suggest inflammation is well controlled.
How the Test Works
- The patient inhales, then exhales slowly and steadily into the mouthpiece, guided by on-screen prompts on the NObreath’s touchscreen.
- The device measures nitric oxide concentration during the controlled exhalation (roughly 12 seconds for adults, 10 seconds for children).
- A single numerical ppb value appears immediately — no lab processing, no waiting for results.
What the Results Mean
A commonly used clinical reference point is a FeNO reading above 50 ppb, which can indicate significant eosinophilic airway inflammation and support a diagnosis of asthma or signal poor control in a diagnosed patient. Results are typically interpreted alongside clinical history, spirometry, and symptom scores — FeNO is a complementary tool, not a replacement for a full respiratory work-up.
Why FeNO Testing Matters for Asthma Care
- Diagnostic support: Helps distinguish asthma from other causes of respiratory symptoms when the clinical picture is unclear.
- Treatment monitoring: Tracks whether inhaled corticosteroid therapy is reducing airway inflammation over time.
- Reducing over- or under-treatment: Objective data can support step-up or step-down decisions on steroid dosing, rather than relying on symptoms alone.
- Pediatric-friendly: Quick, non-invasive, and requires only steady breathing — no forced exhalation like spirometry — making it easier to perform in children.
Guideline Recognition
FeNO testing is referenced in NICE’s NG245 guideline on asthma diagnosis and monitoring, and is supported by the American Thoracic Society (ATS) and European Respiratory Society (ERS), as well as British Thoracic Society/SIGN guidelines. Clinics adopting FeNO testing are aligning with an internationally recognized diagnostic pathway.
The Case for FeNO Testing
Why FeNO Testing Strengthens Your Asthma Practice
- Objectively measures eosinophilic airway inflammation, rather than relying on patient-reported symptoms alone
- Helps confirm an asthma diagnosis in ambiguous cases where spirometry appears normal between flare-ups
- Predicts and monitors patient response to inhaled corticosteroid (ICS) therapy
- Reveals poor inhaler technique or non-adherence — FeNO stays elevated if ICS isn’t being taken effectively
- Helps distinguish asthma from look-alike conditions (e.g., vocal cord dysfunction, chronic cough from other causes)
- Non-invasive, takes about a minute, and is well-tolerated even in children
- Recognized in NICE (UK) and ATS/ERS international guidelines as part of standard asthma diagnostic workup
What’s Genuinely Difficult Without It
- Diagnosis relies on symptoms and spirometry, both of which can appear normal between attacks — especially in mild or intermittent asthma
- No objective way to confirm whether a patient is actually responding to steroids, or simply not taking them correctly
- Higher risk of treating a non-asthma cough or wheeze as asthma, leading to unnecessary steroid exposure
- Step-up/step-down treatment decisions rely more on guesswork than on a measurable inflammation marker
- Harder to detect early in children who may struggle to perform reliable spirometry
See the device we supply → The NObreath Monitor